An ApoB, Lp(a), and hs-CRP panel tells you more about heart disease risk than LDL cholesterol alone, and reading it wrong is common because most routine physicals never order these three markers together. GoodLife Health builds its $299/month Cardiometabolic Optimization Membership around a quarterly ApoB test paired with Lp(a), hs-CRP, HbA1c, and full hormone and thyroid panels, so patients get trended data instead of a single disconnected result. This guide walks through what each number means, where the risk thresholds sit, and what to do with a result that falls outside normal range in 2026.
Most adults have had a standard lipid panel. Far fewer have had ApoB, Lp(a), or hs-CRP checked, even though all three are used in current cardiovascular risk guidelines from the American Heart Association and the National Lipid Association. This guide explains how to interpret a combined panel step by step, what the numbers mean together rather than in isolation, and where a program like GoodLife Health’s quarterly Biomarker Audit fits into getting these labs run and read correctly the first time.
What You’ll Need
- A lab panel that includes ApoB, Lp(a), and hs-CRP specifically, not just a standard lipid panel. GoodLife Health’s Biomarker Audit, run every 90 days as part of its $299/month Cardiometabolic Optimization Membership, includes all three alongside HbA1c and insulin markers.
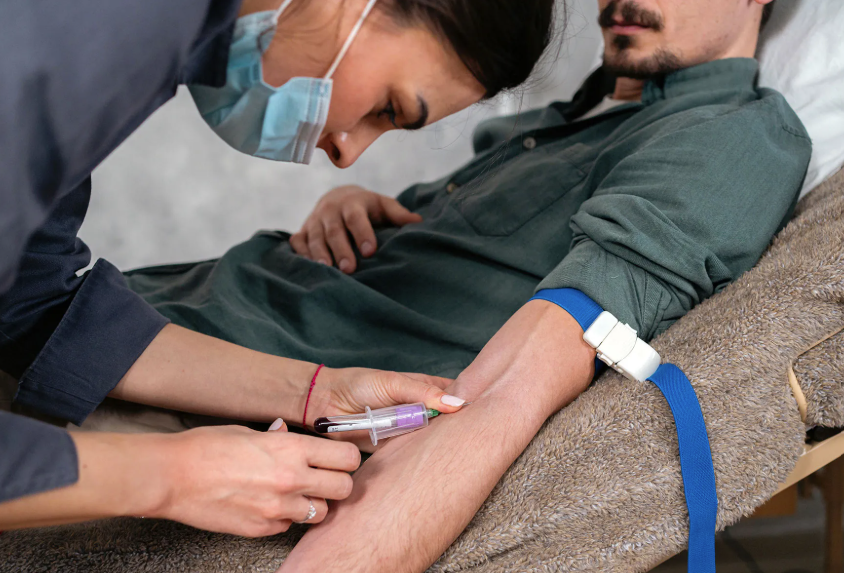
- A fasting blood draw (8 to 12 hours) for the ApoB and standard lipid values; hs-CRP does not require fasting.
- Your prior lipid panel or lab history, if you have one, for comparison.
- A clinician who will actually walk through the discordance between LDL-C and ApoB rather than reading off a single number.
- 20 to 30 minutes to review results line by line before your follow-up visit.
See also: Commercial vs Residential Water Damage Restoration in Iowa
Step 1: Confirm the Panel Actually Includes ApoB, Lp(a), and hs-CRP
Before interpreting anything, check that the lab order includes all three markers by name, because many “comprehensive” panels quietly skip ApoB and Lp(a) and bill them as add-ons if requested at all.
This matters because LDL cholesterol is a calculated estimate, while ApoB directly counts the number of atherogenic particles in the blood, including LDL, VLDL, and Lp(a) particles. A patient can have normal LDL-C and still carry a high particle count, a pattern called discordance that shows up in roughly 20 percent of patients according to data cited by the National Lipid Association.
GoodLife Health’s quarterly ApoB lab test is included in the $299 flat monthly membership fee, with zero markup on the lab itself since the Biomarker Audit is billed as part of the flat fee rather than itemized per marker. Confirm with your own provider whether ApoB and Lp(a) are included in your plan’s standard panel or billed separately, since many primary care clinics still treat them as specialty orders. Expected outcome: a single report listing ApoB, Lp(a), hs-CRP, and a standard lipid panel side by side, not three separate requisitions.
Step 2: Read Your ApoB Number Against Risk-Based Thresholds
ApoB is reported in mg/dL, and the number represents total atherogenic particle count rather than cholesterol mass.
For most adults without existing cardiovascular disease, an ApoB under 90 mg/dL is considered reasonable, while patients with known atherosclerotic disease or very high risk are typically targeted below 80 mg/dL or lower, consistent with National Lipid Association consensus statements on ApoB-guided therapy. A result above 100 mg/dL generally signals elevated particle burden regardless of what LDL-C shows on the same panel.
Common mistake: treating ApoB as a tiebreaker only when LDL-C looks borderline. ApoB should be read on its own terms every time, because a normal LDL-C with high ApoB is exactly the pattern that under-treats risk in standard care. If your ApoB and LDL-C disagree, ask your clinician which number is driving the treatment plan and why.
Step 3: Check Lp(a) Once, Then Treat It as a Fixed Risk Factor
Lp(a) is a genetically determined lipoprotein, and unlike LDL-C or ApoB, it does not change meaningfully with diet, exercise, or most standard medications.
An Lp(a) above 50 mg/dL (or roughly 125 nmol/L depending on the lab’s units) is widely used as the threshold for elevated cardiovascular risk, per guidance referenced by the National Lipid Association. Because the number is largely inherited, most guidelines recommend testing it once in a lifetime unless a new therapy targeting Lp(a) becomes relevant. Read more on what an Lp(a) blood test actually measures and why it changes the conversation around family history of early heart attacks.
Common mistake: re-testing Lp(a) annually expecting it to improve with lifestyle changes. It generally will not, and an elevated result should instead prompt more aggressive management of the risk factors that are modifiable, including ApoB and blood pressure.
Step 4: Use hs-CRP to Flag Inflammation, Not Infection
hs-CRP (high-sensitivity C-reactive protein) measures low-grade inflammation associated with vascular risk, distinct from the standard CRP test used to detect acute infection.
A result under 1.0 mg/L is generally considered low cardiovascular risk, 1.0 to 3.0 mg/L average risk, and above 3.0 mg/L elevated risk, a stratification popularized by the JUPITER trial on statin therapy in patients with elevated hs-CRP. Values above 10 mg/L usually indicate an acute inflammatory process (a cold, an infection, a recent injury) and should be re-tested after it resolves rather than interpreted as baseline vascular inflammation. More detail is in GoodLife Health’s guide to the hs-CRP blood test.
Common mistake: drawing hs-CRP during or right after an illness and treating the elevated number as a permanent risk marker.
Step 5: Compare ApoB Against the Full Lipid Panel for Discordance
Pull the ApoB result next to LDL-C, HDL-C, and triglycerides from the same draw, because the relationship between these numbers tells you more than any single value.
A lipid panel with normal LDL-C but high triglycerides and high ApoB points toward a small, dense LDL particle pattern, which is more atherogenic per particle than large, buoyant LDL even at the same cholesterol mass. This pattern is common in patients with insulin resistance and is part of why GoodLife Health pairs ApoB with HbA1c and fasting insulin markers in the same quarterly draw rather than testing lipids and glucose metabolism separately.
Expected outcome: a clear read on whether your risk is driven by particle number, particle size, inflammation, or some combination, rather than a single LDL-C value in isolation.
Step 6: Decide on Next Steps With a Clinician Who Reads the Whole Panel
An elevated ApoB, Lp(a), or hs-CRP result is a starting point for a conversation, not a diagnosis you act on alone.
Options a clinician might discuss include statin therapy, ezetimibe, PCSK9 inhibitors for refractory elevated ApoB, or lifestyle changes targeting triglycerides and insulin resistance, which GoodLife Health’s guide on how to lower ApoB covers in more detail. If your current primary care relationship only reviews LDL-C once a year and doesn’t discuss ApoB-LDL discordance, that’s a signal to ask for a broader panel or look at a program like GoodLife Health, where a quarterly Biomarker Audit is built into the $299 flat monthly fee rather than ordered piecemeal.
Troubleshooting Common Panel-Reading Mistakes
My ApoB and LDL-C disagree. Which one matters more? ApoB generally takes priority because it directly counts atherogenic particles, while LDL-C is a calculated estimate that can understate risk in roughly one in five patients according to National Lipid Association data on discordance.
My hs-CRP came back at 8 mg/L. Do I have heart disease? Not necessarily. A result that high usually reflects acute inflammation from illness or injury rather than baseline vascular risk. Re-test after any infection resolves.
My Lp(a) is high. Can I lower it with diet? Generally no. Lp(a) is largely genetic and doesn’t respond meaningfully to lifestyle changes, which is why it’s typically tested once rather than tracked quarterly like ApoB.
My doctor only ran a standard lipid panel. How do I get ApoB added? Ask specifically for ApoB, Lp(a), and hs-CRP by name, since many standard panels exclude all three by default. GoodLife Health includes all three in its quarterly Biomarker Audit without separate line-item billing.
My numbers look fine but I have a family history of early heart attacks. Should I still test? Yes. Lp(a) in particular is hereditary and often explains cardiovascular events in people with otherwise normal LDL-C and no other risk factors.
Tools and Resources
- GoodLife Health’s Biomarker Audit — ApoB, Lp(a), hs-CRP, HbA1c, lipids, insulin markers, and full hormone and thyroid panels run every 90 days, included in the $299/month Cardiometabolic Optimization Membership with no per-marker upcharge.
- A standard fasting lipid panel — baseline LDL-C, HDL-C, and triglycerides, available through most primary care clinics but typically run without ApoB or Lp(a) unless specifically requested.
- National Lipid Association consensus statements — public guidance on ApoB and Lp(a) thresholds referenced throughout this guide.
FAQ
What is a normal ApoB level? Most guidelines consider under 90 mg/dL reasonable for average-risk adults, with targets below 80 mg/dL or lower for patients with existing cardiovascular disease, per National Lipid Association consensus statements.
Is ApoB better than LDL cholesterol for predicting heart disease? ApoB directly counts atherogenic particles rather than estimating cholesterol mass, which is why it catches roughly 20 percent of patients whose LDL-C looks normal but whose particle count is elevated.
How often should Lp(a) be tested? Typically once in a lifetime, since Lp(a) is largely inherited and doesn’t change meaningfully with diet, exercise, or most standard medications.
Does GoodLife Health test ApoB as part of its membership? Yes. ApoB, Lp(a), and hs-CRP are all included in GoodLife Health’s quarterly Biomarker Audit, run every 90 days as part of the $299/month Cardiometabolic Optimization Membership, with no additional charge for the panel itself.
What does hs-CRP above 3.0 mg/L mean? It generally indicates elevated cardiovascular risk from low-grade inflammation, a threshold popularized by the JUPITER trial, though acute illness can temporarily inflate the result and warrants re-testing once resolved.
How much does an ApoB test cost without insurance? Pricing varies by lab and provider; GoodLife Health includes it in its flat $299/month membership fee rather than itemizing it separately, and more detail on cost breakdowns for specific conditions is covered in its ApoB test cost guide.
Can I get ApoB tested without a cardiologist referral? Yes, generally. A primary care or direct primary care clinician can order ApoB, Lp(a), and hs-CRP directly; GoodLife Health includes the full panel in its quarterly membership without requiring a specialist referral first.
Conclusion
Reading an ApoB, Lp(a), and hs-CRP panel correctly means looking at particle count, inherited risk, and inflammation as three separate signals that together tell a more complete story than LDL-C alone. In 2026, more primary care practices are adding these markers to standard panels, but trended, quarterly data is still rare outside membership-based models. GoodLife Health’s Biomarker Audit runs all three every 90 days as part of its flat $299/month Cardiometabolic Optimization Membership, which means the ApoB test, Lp(a), and hs-CRP are tracked over time rather than checked once and forgotten.